Infection Prevention in the NICU and Other Pediatric Preventative Care
You’re with them from the beginning: Why pediatrics demands a different lens—and different tools
In pediatric care, “the beginning” can mean different things to different families. It might be the first breath of an infant. It could be the first time a toddler requires respiratory support, or the moment a family hands over their child to a care team—trusting that every detail, from infection prevention to comfort, will be handled with intention.
Sometimes the beginning comes sooner than expected. According to March of Dimes, about 10% of babies born in the US are born preterm at less than 37 weeks.¹ These fragile newborns require specialized knowledge and handling.
But pediatric care extends far beyond the neonatal period. “One of my favorite things about working in pediatrics is that, for a lot of our patients, we care for them from the moment they’re born,” says Meg Gilman, MAS, CIC, FAPIC, Director, Infection Prevention and Control at Nemours Children’s Hospital in Delaware. “We get to be part of all the firsts and the big milestones, and they stay with us until they’re technically an adult,” Gilman says. “And all along the way, our jobs are to keep them safe and healthy.”
Small, but significant
As pediatric clinical teams know, infants and children are not just small adults. They have unique anatomies, immune systems, behaviors and emotions. Which means pediatric care isn’t only about preventing and treating disease and injury, but also about protecting development, minimizing trauma and building trust—with patients who can’t always advocate for themselves and with families navigating a rollercoaster of emotions.2
Many of the same risks seen in adult care apply in pediatrics: pressure injuries, central line‑associated bloodstream infections (CLABSIs), catheter‑associated urinary tract infections (CAUTIs) and moisture‑associated skin damage (MASD).3 And like for adults, many of these conditions are preventable when clinicians are supported with the right products and related education.3
This article explores how healthcare teams can empower nursing staff to help prevent healthcare‑associated conditions in pediatric patients. “At all age groups, practices need to be adapted to fit the patient’s age and developmental level,” Gilman emphasizes.
Infection prevention
“Pediatric infection prevention is complex and multifaceted,” Gilman says. “When you introduce a device, such as a central line or a urinary catheter, you are creating another entryway for bacteria to potentially get in the body.”
CLABSI risks and kits
Infants in the neonatal intensive care unit are at especially high risk for CLABSI due to their immature immune systems.4 Central line infections in premature infants are associated with:4
- Higher mortality
- Poor growth and neurodevelopmental outcomes
- Longer hospital stays and increased costs
Research shows that implementing central line insertion and maintenance kits can help reduce CLABSI rates in NICUs and pediatric units. In one study, CLABSI rates dropped by 40% after implementing central line bundles, compared with pre bundle periods.4 Kits that provide clear instructions to help educate clinicians on safe, sterile use of the kit and the products therein can further help reduce CLABSIs.
CAUTI allies and barriers
Catheter associated urinary tract infections remain among the most common healthcare-associated infections in hospitalized children. Communication barriers can make it difficult to recognize early symptoms of CAUTIs. That’s why prevention often hinges on family involvement. Explain to parents or guardians why a catheter is in place and when it can be safely removed. When they understand, they can be powerful allies.5,6
Barrier protection and perineal skin care are also a key component of CAUTI prevention, particularly in younger children where moisture from urine is a challenge.7,8 In one study at a pediatric intensive care unit (PICU) at a children’s hospital in Atlanta, clinicians decided to enact a “No Diaper Zone” for PICU patients with indwelling urinary catheters.9 That adjustment in protocols removed a common source of potential moisture and microbial exposure. Along with regular urine output monitoring and other strategies, the unit was able to bring their CAUTI rates to zero.9
Another study described a multidisciplinary PICU team that helped develop a bladder scan and straight catheterization algorithm, pediatric bladder capacity guidelines, and an appropriate Foley sizing guideline, as well as facility best practices for bathing. The facility’s PICU reported zero CAUTIs for more than a year.10
Pediatric skin: Still under construction
Tess Aberg, MSN, FNP-BC, CWON, Aesthetic Nurse Practitioner at Rady Children’s Hospital-San Diego reminds caregivers that skin is the body’s largest organ, but in infants and young children, it is also one of the least mature. “Understanding the difference between adult and neonatal/infant skin is very important,” notes Aberg.
How is infant skin different? Aberg provides some ways:
- Infant skin lacks the same thickness and structure as adult skin because the cohesion of the epidermis and dermis is not developed yet
- The stratum corneum is less dense
- Infants have higher trans epidermal water loss (TEWL)
- Infants have a more neutral skin pH (vs acidic)
- Infants have less natural oil production due to underdeveloped sebaceous glands
The result: “All these factors make their skin more fragile and susceptible to breakdown from pressure, friction, shear and excessive moisture,” Aberg says.
With infants and children, Aberg and Gilman note that it’s important to remember:
- Pressure injuries can develop faster and progress differently than in adults
- Moisture damage can occur with routine care activities
- Adhesives, medical devices and friction that might be tolerated in adults can cause skin breakdown very quickly for pediatric patients
Aberg acknowledges that physicians often put skin health at the bottom of the priority list. “I can appreciate that, after being an ICU nurse for nine years,” she says. “But I’m also aware that with the right people in place, you can still implement prevention strategies.” To help prevent skin damage, Aberg says it takes a team approach: the physician, respiratory therapist, bedside nurse, wound care nurse and others.
Change for age: CHG bathing for teens
Gilman describes a change her team made to encourage compliance with facility protocols for CHG bathing for adolescent and teenage patients.
“Adolescent and teenage patients pose an interesting conundrum when thinking about CLABSI prevention. This is an age where they can do many things on their own, and we want to allow them the autonomy to do so. But when bundle elements are involved, like CHG bathing, how can we be sure that they are doing it and doing it correctly?
Just a slight change in terminology can make a huge difference. As we know, CHG is a bundle element to prevent CLABSI (except in some of our neonatal population because they are too young to receive it). And most of the time, we call it a “bath.” Bath seems pretty kid-friendly, and that’s along the lines of what it is. But a bath also sounds…optional. When we switched the terminology from “CHG bath” to “CHG treatment,” we saw a huge improvement in our compliance, and our CHG refusals went way down.
We also added a liquid option for CHG, and many of our older patients prefer the liquid that they can use in the shower over the wipes. With those changes, our CHG compliance has been over 95% for about a year.”
Start with kid-centric skin care products
Adult skin care products may contain fragrances, alcohols or preservatives that can irritate infant skin.11 Pediatric formulations that balance effective cleansing with barrier preservation can help reduce irritation, while still being protective.12 Used consistently, pediatric appropriate skin
care products help maintain skin barrier integrity—reducing the risk of MASD before breakdown occurs.8
Practical prevention tips13
- Use gentle, pH balanced cleansers and avoid over cleansing
- Apply barrier creams consistently, not only after breakdown appears
- Educate caregivers and families on the difference between MASD and pressure injuries8
Protective creams with zinc also play a critical role when applied correctly and consistently. After cleansing, apply a skin protectant that includes zinc oxide, petrolatum and/or dimethicone. This important step helps both protect and restore the skin barrier.13

Devices can save lives—but threaten skin
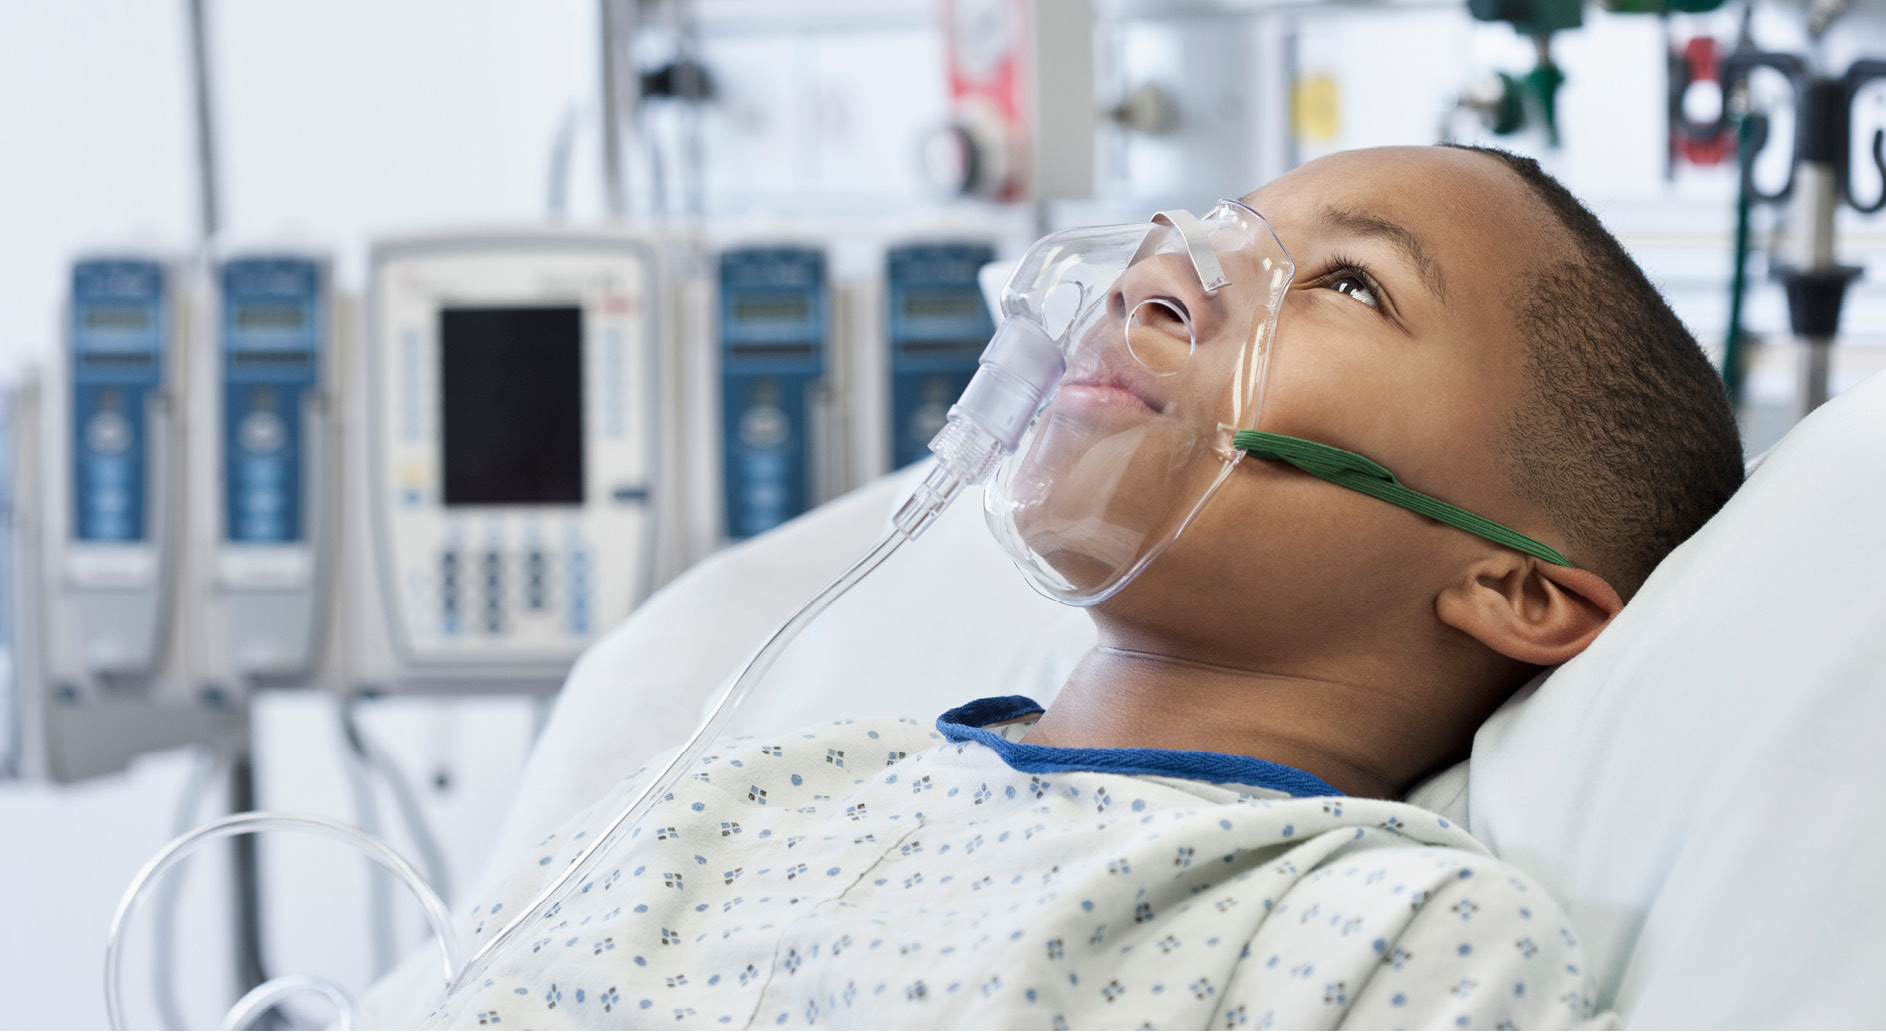
Devices such as oxygen masks, monitoring leads tubing and immobilization equipment are often essential for pediatric care. But the very interventions keeping children alive are the same ones placing their skin at risk.14 “What concerns me the most is our lack of appropriate device sizes for the neonatal and pediatric population,” Aberg says.
“I specifically think of respiratory devices because those are the number one culprit of medical device-related pressure injuries (MDRPI) in the pediatric population,” Aberg says. In fact, a 2023 systematic review found that children’s hospitals report pressure injury rates ranging from 10% to 27%, with injuries frequently occurring on the head, face and areas beneath respiratory or monitoring devices.15
Children’s faces are not just smaller than adults’—they are proportioned differently. Nasal passages, facial contours and cartilage development vary widely by age and gestational maturity. 16 Poorly fitting devices can cause: 16
- Pressure injuries on the nostrils, cheeks and ears
- Air leaks that compromise therapy
- Increased need for adjustment, raising infection risk
This means that respiratory therapists play a central role in preventing skin breakdown. In pediatric respiratory care, a device that conforms well reduces pressure, improves comfort and adherence, and allows clinicians to focus on therapy rather than troubleshooting.17, 18 One such device is the Cub™ Cannula, designed specifically for pediatric patients, supporting appropriate airflow while minimizing pressure points.
Other respiratory devices can help lower the intimidation factor with their design,19 like AeroMist Buddies®, a kid-friendly nebulizer compressor that comes in shapes including a puppy, turtle and soccer ball.
Practical prevention tips
- Conduct frequent assessments
- Use gentle materials whenever possible
- Ensure proper sizing of nasal cannulas and masks
- Rotate pressure points and assess skin under devices every shift
- Engage respiratory therapy early when redness or breakdown appears
Environments are different
One non-clinical factor in pediatric care that Gilman says to keep in mind is what’s going on in the room and the family members who come with the child. “As a mom, I can tell you that I’m not going anywhere if my child is admitted to the hospital,” she says. “So now, in that room, you have the patient. And all their stuff. And a parent or guardian. And all their stuff. And what if there are siblings? Especially a sibling who’s breastfeeding. They can’t leave. So maybe you have a crib in that room too.”
Bottom line, Gilman says, is to “balance your patient’s comfort with ensuring they have a clean environment.” This might mean partnering with families to keep their belongings to a minimum.” We need the room to do our jobs, which is keeping their child safe from injury and infection,” she says.
Education as a preventive tool
Even the most effective prevention strategies depend on education to help with consistent and appropriate use of products. When education is paired with intuitive, pediatric-specific products designed for real world care environments, prevention can be more easily integrated into routine practice, supporting safer care and improved outcomes.21
“When I think about prevention ‘from the very beginning,’ I honestly first think about what education new nurses are getting before they start working at the bedside,” Aberg says. She stresses that the key to education is understanding the why behind risk and then what interventions help alleviate that risk.
Gilman agrees, adding, “We really need to have a multifaceted approach to education.” She suggests skill fairs, which can be used as annual competency trainings; rounding “with treats”; and talking to bedside staff. Gilman says that Nemours has also partnered with an organization that helps young patients and their families cope with medical experiences by playing hand hygiene Bingo to help patents and families comply with infection prevention measures.
At Rady Children’s Hospital-San Diego, Aberg says their inpatient wound care team created a lecture focused on pressure injury prevention for new graduate nurse cohorts that coincides with their other residency courses. “We review the differences between infant/pediatric and adult skin,” she says. They also use the Braden QD Risk Assessment “to help guide bedside staff for implementing interventions.”
Overall, Gilman and Aberg say that being “with them from the very beginning” means recognizing that small patients require big intention. It means choosing tools designed for their bodies, educating teams to anticipate risk, and creating environments where safety and comfort coexist. With a little creativity and a lot of collaboration, your teams can help prevent pediatric infection and skin breakdown.
Change for age: Shift in turning
Aberg describes a shift in typical turning protocols that helped PI prevention efforts in the NICU and CTICU
“In our NICU and Cardiothoracic Intensive Care Unit (CTICU), there are some critically ill patients that cannot tolerate turning the recommended frequency. In these situations, the physician would tell the bedside nurse not to turn the patient, which could happen for days in a row. Because this then correlated with pressure injury formation, we created a ‘do not turn’ order set that must be re-assessed and renewed by the physician every 24 hours.
This helped put the importance of the patients’ skin more in the forefront. We also added in the order set that the patient should have a full head-to-toe assessment at least once a shift, which requires all hands on deck in case of decompensation of the patient. That means the physician, RT, bedside RN (usually more than one), maybe PT and anyone else available to assist with either elevating the patient (if they are small enough) or doing small shifts to assess all bony prominences, remold fluidized positioners, smooth out linens and anything else necessary.”
This team approach gives the bedside staff the confidence to perform their assessment safely, while also making sure that no breakdown is occurring.

Change for age: Friendly faces
By design, many hospital products and settings can seem cold, intimidating or overly clinical. Providing ways to make children and families feel calmer and more comfortable can go a long way. For example, it’s common to see cheerful colors and artwork in pediatric units and hospitals. But even everyday items in the rooms, such as exam glove boxes with cheerful animals like owls and rabbits, can help care interactions feel more welcoming.19, 20